The Use of Aromatherapy in Palliative and Supportive Care
by Terry Bartley
Introduction
I work as a Care Assistant in a Residential Home, also giving aromatherapy massage to some of the residents. The effects on the residents receiving massage are immediate and positive, prompting me to research the effects of aromatherapy massage in palliative and supportive care.
More and more patients with cancer, other chronic illnesses or who are terminally ill are demanding a more holistic approach to their treatment, an approach that takes into account their physical, mental, emotional and spiritual wellbeing. Complementary therapies, especially aromatherapy, therapeutic touch and homeopathy, are becoming more widely available to these patients and the medical profession is carrying out controlled well-conducted studies to research the effectiveness of these therapies in supportive and palliative care.
What is Palliative Care?
Palliative means to cover or cloak. Palliative care is the care of terminally ill people by covering or cloaking their symptoms when there is no known cure. In practice, this means managing the illness through the relief of pain and other physical symptoms and improving the quality of life.
Palliative care in hospitals deals primarily and almost exclusively with the physical aspects using conventional medicines. Treatment may be very clinical with the environment possibly sterile and “soulless”. The priority in hospitals is to treat the condition, looking to the future and the healing the patient. The staff, though very caring and sympathetic, are often busy with a heavy workload and the pressure of targets.
In the 1960’s, the modern hospice movement was set up. The aim of this movement is to improve the quality of end of life and the quality of death for their patients in a relaxed, friendly and non-clinical environment. The care and treatment of the patient is in the present, the here and now, and on all levels – physical, mental, emotional and spiritual. The staff are specially trained in palliative care and work empathetically with their patients.
Why use Aromatherapy in Palliative Care?
In Palliative care, “healing” takes on its ancient meaning of “Whole” or “holy”. So “healing” is the letting go of the desire to achieve health and accepting death, facing it calmly and without fear or pain. Management of pain and other physical symptoms by medication is relatively simple in this day and age of technology and scientific and pharmacological advancement. But palliative “healing” is not merely physical, but emotional, mental and spiritual. Complementary therapies work on these levels and integrating them into the clinical environment achieves a holistic care programme that can truly improve the quality of life and the quality of death.
Aromatherapy may be helpful:
- To promote relaxation
- To alleviate anxiety
- To reduce depression
- To reduce pain
- To reduce nausea
- To alleviate physical symptoms
- To alleviate side effects of chemotherapy
- To improve sleep patterns
- To reduce stress and tension
- To alleviate psychological distress/provide emotional support
- To improve well-being and quality of life
- To live with altered body image
National Guidelines
Through the Prince of Wales Foundation for Integrated Health Care, and the National Council for Hospice and Specialist Palliative Care, Marianne Tavares has written and published the National Guidelines for the Use of Complementary Therapies in Supportive and Palliative Care.
These guidelines support clinical guidelines and address issues relating to the safety of patients in the provision of complementary therapies, including clinical governance, regulation and training of therapists, audit and evaluation.
For aromatherapy and massage the guidelines advise:
- The patient must be aware of what the treatment is and how it can affect them, including any possible side effects. The patient must give consent.
- Therapists with limited experience must have further training and supervision from therapists with experience in the use of supportive and palliative therapy.
- Infection Control.
The therapist must:
- Follow good basic hygiene practices
- Cover all their own grazes, cuts with waterproof dressings
- Use disposable aprons and gloves when dealing with any spillages of bodily fluids
- MRSA – gloves, aprons and hand washing are particularly important in treating patients with MRSA.
4. When treating the patient:
- Avoid using any pressure directly on the area of cancer
- Avoid pressure work with patients who are taking anti-coagulation medication or who have low platelet counts.
- Avoid a limb or foot with suspected or recent deep vein thrombosis and be aware of the signs and symptoms
- Avoid areas of bony metastases
- Avoid stoma areas, dressings, catheters and tens machines
- Be aware of patients with lowered immune functions, as they are more susceptible to infections
- Be aware that skin can be sensitive and/or paper thin due to medication, treatment and especially in the elderly.
5. Oils.
- Oils must be bought from a recognised supplier, with a data sheet that must be filed.
- Stored in a locked cupboard, away from heat and sunlight, in airtight, clearly labelled bottles. Used within one year of purchase or by the date on the label.
- Oils should only be mixed and used by experienced aromatherapists following an assessment of the patient for contraindications with the clinical team as an integrated approach.
- Strength of the blend must be 1% or less for massage and to a 1% dilution in a non-oil based medium before being added to a bath to prevent neat oil coming into contact with the patient’s skin.
- If a carer or family member is administering a massage to the patient, either hand or foot, the aromatherapist must still mix the oil.
- If the oils are to be used in a vaporiser, staff who may be replenishing the vaporiser must be fully trained in that use.
6. Spillage and breakage.
- Wear gloves and soak up the oil with paper towels. All bottles, either empty or broken, must be disposed of in a sharps bin. The paper used to soak up the oil should be put in a polythene bag and disposed of.
- Skin that has come into contact with undiluted oil and has reacted needs to be diluted with carrier oil then washed with unperfumed soap.
- If the oil comes into contact with the eye, irrigate with oil then water.
- If oil is swallowed, drink a little milk.
- In all these circumstances, seek medical help and keep the bottle and data sheet for the information of the medical assistance.
Evidence Base
The recognition that touch and massage can have therapeutic value dates back to the Yellow Emperor’s Classic of Internal Medicine (cc. 250bc), Sanskrit texts, Homer’s Odyssey,
Hippocrates, Galen in the middle ages and Paracelsus in 15th century. Massage especially gives physiological and psychological benefits for palliative care patients.
The need for an evidence base for complementary therapy has been clearly articulated in the House of Lords Select Committee on Science and Technology report on Complementary and Alternative Medicine. (2000).
The results from Wilkinsons et al’s (1999) study with 103 cancer patients suggest that Aromatherapy massage reduces anxiety in patients with advanced cancer. Grealish et al (2000) measured the short-term effect of foot massage on 87 hospital patients. It was found that there was an immediate effect on reducing pain and nausea and encouraging relaxation.
In a study on palliative day care, the patients receiving aromatherapy had a greater sense of well being and wished to continue with the therapy, but due to the fact that the patients were terminally ill, it was not possible to conclude any long term benefits. Short term effects were psychological more that physiological.
From these and other researches, it can be concluded that aromatherapy massage is an acceptable intervention for cancer patients.
Practical Use
Whether aromatherapy is being given in hospitals, hospices or for the care of patients in their own homes, it is essential that the same procedures and safeguards are used.
Contraindications
Oncologists have stated that there is no evidence that massage increases the spread of lymphoma or leukaemia cells and that cancer is not a contraindication to receiving gentle massage. Cancer can spread whilst a body is at rest or even asleep and gentle massage does not increase vascular or lymphatic circulation any more than the activities of daily living.
In the case of Deep Vein Thrombosis, only massage hands and face as massage can increase circulation sufficiently to move emboli. Hand and face massage done lightly will help to reduce anxiety without these adverse effects.
There are no contraindications with diabetes, but pressure should be light to prevent bruising or the thin skin tearing which could result in a diabetic ulcer.
Use a low dilution – 1% -, as the skin of the elderly is thin, dry and absorbent. The metabolism is slower in the elderly so it is prudent to keep the dosage low especially if the patient is on long term medication.
Risk Assessments
The patient needs to be assessed for suitability for treatment. This risk assessment must be carried out by a multi-disciplinary team, taking into account the patient’s condition, medication, contraindications such as heart disease, epilepsy, DVT and any possible side or adverse effects.
If it is decided that aromatherapy is not appropriate treatment, this must be documented in the patient’s records, with the reasons for that conclusion.
If aromatherapy treatment is appropriate and recommended then the aims and objectives of that intervention are documented, including any problems.
Consent
If a patient consents to a therapy, they must have been provided with sufficient information to enable them to make an informed and considered decision.
Department of Health guidance (2001) is helping to provide clarity about the issue of consent. For example, in the case of a competent adult, treatment can begin once the patient has given verbal consent after being given a brief explanation about their treatment.
Record Keeping
Therapists must keep records of all the patients admitted to the hospice, hospital, care home or referred for treatment.
These records contain the information of all the essential oils and the carrier oils used on that patient and any possible side or adverse effects. The records will also contain risk assessments carried out on that patient – the results of any patch tests carried out for allergic reactions and any contraindications such as heart disease, epilepsy, pacemakers, or any major surgery.
Patients are treated regularly at intervals decided by the multi-disciplinary team and records kept of each treatment session, including:
- The oils used
- Length of treatment
- Method of administering – massage, inhalation, vapouriser (in the case of massage, which area of the body)
- Feedback from patient
- Care Plans – These are set up when a patient is first admitted to hospices or residential care or nursing homes. These contain the medical history of the patient, their personal details and their ongoing daily care, medication, diet, activities, hygiene routine. The records kept by the aromatherapist are included into these care plans. In this way, the care of the patient is fully integrated.
All records are subject to the Data Protection Act 1998 and patient confidentiality extends to the use of complementary therapies.
Education
It is important that the patient, their family and carers are familiar with aromatherapy, its benefits and possible side effects. A literature folder consisting mainly of research articles can be kept in the hospice for the staff to read. This helps staff to discuss the treatment with the patient’s family in an informed and unbiased way.
Method of administering the oils
Massage will need to be very gentle and only on hands, feet and maybe the face. Sessions will need to be very short, from a few minutes to 10 minutes at the most. Dilution must be 1% or less.
Baths may be possible in some cases, but the oils must be diluted prior to adding to the water to prevent any possibility of neat oil coming into contact with the patient’s skin.
Burners and inhalation can often be used, especially once the patient gets to the point where massage is no longer possible or enjoyable. In these cases, the choice of oil can be left more to the patient. Placing a drop of oil on a handkerchief is a simple way of allowing the patient to experience the aroma and its benefits whenever they like or feel the need.
Palliative care is where subtle Aromatherapy comes into its own
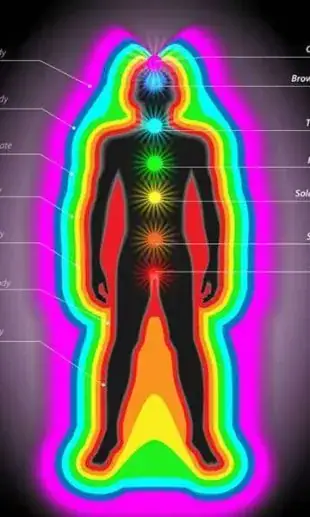
Subtle Aromatherapy works on the spiritual and psychic levels of healing. Once a patient has reached their end of life, working on the level of the higher self helps the emotional, mental and spiritual come to terms with the physical and so helps the patient reach acceptance and so attain calmness, tranquillity and lack of fear.
Because subtle Aromatherapy can be done without physical contact by massaging the aura and balancing the chakras, this treatment is often more acceptable by the patient who may not be able to stand a physical massage, even if this is done very gently. Because of their condition, most patients in hospices or receiving palliative care can only be treated for very short periods, from 2 to 10 minutes.
At the major time of transition that we call death, subtle aromatherapy can be a comfort and support to the dying person, their family friends and their carers. It is especially beneficial when physical treatment is no longer effective. The use of certain oils can help bring acceptance, tranquillity and even joy to the patient.
Effective Oils
Oils that help palliative care patients are those that can help the patient to connect with their higher self and the Divine and to let go of all earthly attachments:
- Frankincense – helps to connect to our higher self
- Cedarwood – helps to strengthen our connection to the Divine
- Angelica – helps to open our minds to the angelic realm
- Rosewood – helps to open the crown chakra and strengthen spirituality
- Neroli – helps strengthen spirituality, go through change
- Cypress – helps at times of change, especially the transition from life to death, manage their grief and feelings of loss
Oils relating to the heart chakra are excellent:
- Bergamot – helps to open and balance the heart chakra. It helps to relieve grief and lift the spirit. For the dying patient this is truly a lifting of the spirit to the Light
- Rose – brings comfort and relief from grief, enhancing feelings of love and peace. It is helpful for friends, relatives and carers as well as for the patient, accept their nearness of their death
- Melissa – this oil is one of the most effective in palliative care. It helps to dispel fear and so aids acceptance, both for the patient and their family, friends and carers. Because Melissa relates to the heart chakra it helps to ease shock, because even an expected bereavement comes as a shock when it happens. Melissa also relates to the solar plexus chakra, which is concerned with expression and our will. Melissa helps the patients will to align with the Divine will and so helps acceptance. There are those who say that Melissa oil has helped in remembering past lives. For a dying person to recall past lives helps them to accept the end of their current life, knowing that they will live again.
Carer Care
For a truly holistic approach to palliative and supportive care, the family, friends and carers of the dying person are in need of support, love, reassurance, comfort and healing as well as the patient. The effect of caring for or living with a terminally ill person can be very traumatic and devastating.
A patient can sometimes be very accepting of their condition and the prognosis. However, close family and friends can find it harder to come to terms with the situation and suffer from anxiety, depression and stress. They may also find it hard to talk about their feelings and even talk to the patient about their feelings and practical matters.
False cheeriness is very stressful and can prevent any meaningful communication at a time when, though it is the most difficult, it is most important.
Practical matters like funeral arrangements, finances, legal matters, etc are not discussed. Emotions and feelings are not shared.
This lack of communication can hinder the acceptance of the situation, for the patient and the family, but especially for the family. This in turn can impact on the patient, making them feel stress and anxiety for their family even though they can accept their own situation. And of course, this in turn can make their transition more difficult than it needs to be.
Aromatherapy can help to reduce anxiety and stress, relieve depression and help to release emotions.
Burners with Bergamot or Rosewood can help build a soft atmosphere of openness, helping to ease communication.
Supportive care does not end when the patient’s life ends. The family, friends and carers are still in need of support, even more so.
Aromatherapy massage is a wonderful releaser of emotions, the physical touch of another human who understands and empathises, the aroma of the oils evoking memories. They feel they have permission to let go and show their grief without feeling guilty, they can talk and release all their pent up anger, frustration and feelings of inadequacy without fear of upsetting anyone else. This gives comfort and solace and starts the healing process that is so vital for them at that time.
Professional carers also need to be able to release their emotions, as the caring can be very intense, especially once the patient they have been caring for passes away.
Massage is very reassuring, comforting and relaxing. The scent of the oils can help stimulate the emotions and help the carer to articulate their grief and so move on. Bottling up these emotions is very unhealthy and can lead to serious physical illnesses later in life.
Aromatherapy is still complementary at this time. Counselling and even medical intervention may be necessary for deep grief. An aromatherapist experienced in palliative and supportive care knows their boundaries and when to call in or refer the patient to more specialised and professional help.
The Therapist
A therapist working in palliative care must be experienced in carrying out risk assessments on patient suitability, contraindications, length of treatments, dilution of oils, appropriate oils, the method of administering the oils. But just as importantly, they must be working from a good ethical framework.
The therapist must work with respect, autonomy, non- malfeasance and within their own knowledge. The therapist must be sensitive to and respectful of the patient’s views and beliefs on life after death and religion.
The treatment given is always for the good of the patient, with their well-being as the priority. The therapist must not be in need themselves, as this will affect the therapist/patient relationship, which must be balanced. For the relationship to develop and fully benefit the patient, the patient needs to feel relaxed and safe, trusting the therapist implicitly. The benefits to the therapist are on an energetic level, from the oils and from the positive effects that their treatment has on the patient.
In subtle aromatherapy, the therapist’s intent, calmness and centred-ness are as important in the treatment as the oil used. It is therefore essential the therapist prepares properly beforehand. A short meditation may be very helpful.
After a treatment, the therapist needs to ensure their chakras are closed to a safe level. Although the therapist also receives the benefits of the oils they are using, it is good to have a cleansing, purifying bath to help revive and restore the balance of their own energy.
Therapists working in palliative care also need to ensure that they have a good support network around them in this intense, emotional but very rewarding work. This should include:
- A peer group – other therapists who experience and understand the work and can give support and advise in a non-judgemental and trusting environment
- Peer supervision – for ongoing development and training
- Organisational group – multidisciplinary team for support and sharing on a day to day or regular basis
- Clinical supervision – multidisciplinary team to discuss the patients case
- Regular visits to an aromatherapist are also very beneficial to the therapist. This could be a therapist who is part of the peer group or totally independent
Case Studies
Case Study One
Condition – NH suffers from anxiety. She often feels that the other residents around her do not like her and so she feels lonely and rejected.
Contraindications – Thin skin, dilution of 1% required.
Treatment – A blend of Bergamot and Lavender massaged gently into the hands and feet helps NH to relax. She talks about her feelings, helping to release her emotions.
Feedback – NH reports that after these massages she always has a good nights sleep, waking feeling refreshed and in a much happier frame of mind. This effect may only last a few days, but the treatment is repeated weekly and there appears to be a cumulative affect on her positive and relaxed mood.
Case Study Two
Condition – DC suffers from painful stiffness of the shoulders. This prevents her sleeping well and so she feels tired and depressed.
Contraindications – Dilution of less that 1% is used as the skin is thin and more easily absorbs the oils.
Treatment – Rosemary and Eucalyptus helped to warm the joint and ease the pain. On a second treatment, Ginger, Juniper and Black Pepper were used. The massage was lighter than would be used in a general massage and was applied to the shoulders and upper back. A Lavender pillow was made up to aid relaxation and sleep.
Feedback – DC reported that her shoulders felt warm and relaxed after the massage. She preferred the blend containing ginger, as this evoked pleasant memories of her childhood and mother’s cooking! DC slept well for several nights after the massages. These massages are carried out at two weekly intervals
Case Study Three
Condition – AC suffers from dementia and has short-term memory loss. She becomes very agitated and tearful, forgetting where she is and who the people are around her.
Contraindications – There are no contraindications
Treatment – Bergamot and Rose in a 1% dilution used in a hand massage.
Feedback – AC immediately reacts to the aroma of the oils. She smiles, relaxes and then after a few minutes, starts to talk about things she can remember. The session always ends with AC laughing and smiling. This mood can last for as long as a week. Regular hand massages are therefore very beneficial.
Conclusion
Palliative and Supportive care needs to be holistic in its approach, as dying is itself holistic. Aromatherapy, especially subtle aromatherapy, is a perfect complement to conventional medicine. Hippocrates understood this concept, and now, in modern medicine, we appear to be going full circle back to this understanding.
Palliative care patients who receive aromatherapy are increasingly requesting that the treatment be continued, for themselves and their family. Although the effects may be short term, in the treatment of patients at their end of life, the effects only need to be short term.
And the effect can be dramatic, with fear, anxiety, stress and depression being relieved and replaced with acceptance, calmness and tranquillity, leading to a gentle peaceful transition from life to death. In some cases, the patient can even start to look forward to their last great adventure in this life.
Recommendations
From research carried out and from my own Case Studies there is a positive argument for the effectiveness of aromatherapy as a complementary intervention in the treatment of palliative and supportive care. To ensure that the best therapy is available, further controlled research needs to be carried out with a formal and structured training programme for the continuous professional development of therapists in palliative care.
It is my hope that integrated palliative and supportive care will be available for every person who is in need.
Bibliography
Davis P. (1991) – Subtle Aromatherapy. The C.W. Daniel Company Ltd.
Tavares M. (2003) – National Guidelines for the Use of Complementary Therapies in Supportive and Palliative Care. Prince of Wales Foundation for Integrated Health Care, and the National Council for Hospice and Specialist Palliative Care.
Richardson J. ( 2007) – Complementary therapies: what is the evidence for their use? Nursing Times
Mullins P. (2007) – Aromatherapy Massage: its use in a ward setting. Nursing Times